Understanding and Relieving Gas Pain in Shoulder: A Medical Guide

Have you ever experienced a sudden, sharp ache radiating up to your shoulder blade, only to realize moments later that it coincides with uncomfortable bloating or digestive distress? This seemingly paradoxical symptom is far more common than most people realize, and it is medically recognized as referred pain originating from the diaphragm and gastrointestinal tract. When trapped air accumulates in the digestive system, it can push upward against the diaphragm, irritating the phrenic nerve. This nerve shares neurological pathways with the cervical spine, effectively tricking your brain into perceiving discomfort in the upper shoulder region rather than the abdomen. Understanding the intricate connection between your digestive processes and musculoskeletal symptoms is the first step toward effective relief. In this comprehensive guide, we will explore the anatomical mechanisms behind gas pain in shoulder, identify common triggers, differentiate benign discomfort from serious medical conditions, and provide evidence-based strategies to alleviate the pain safely and efficiently.
Understanding the Anatomy of Referred Shoulder Discomfort
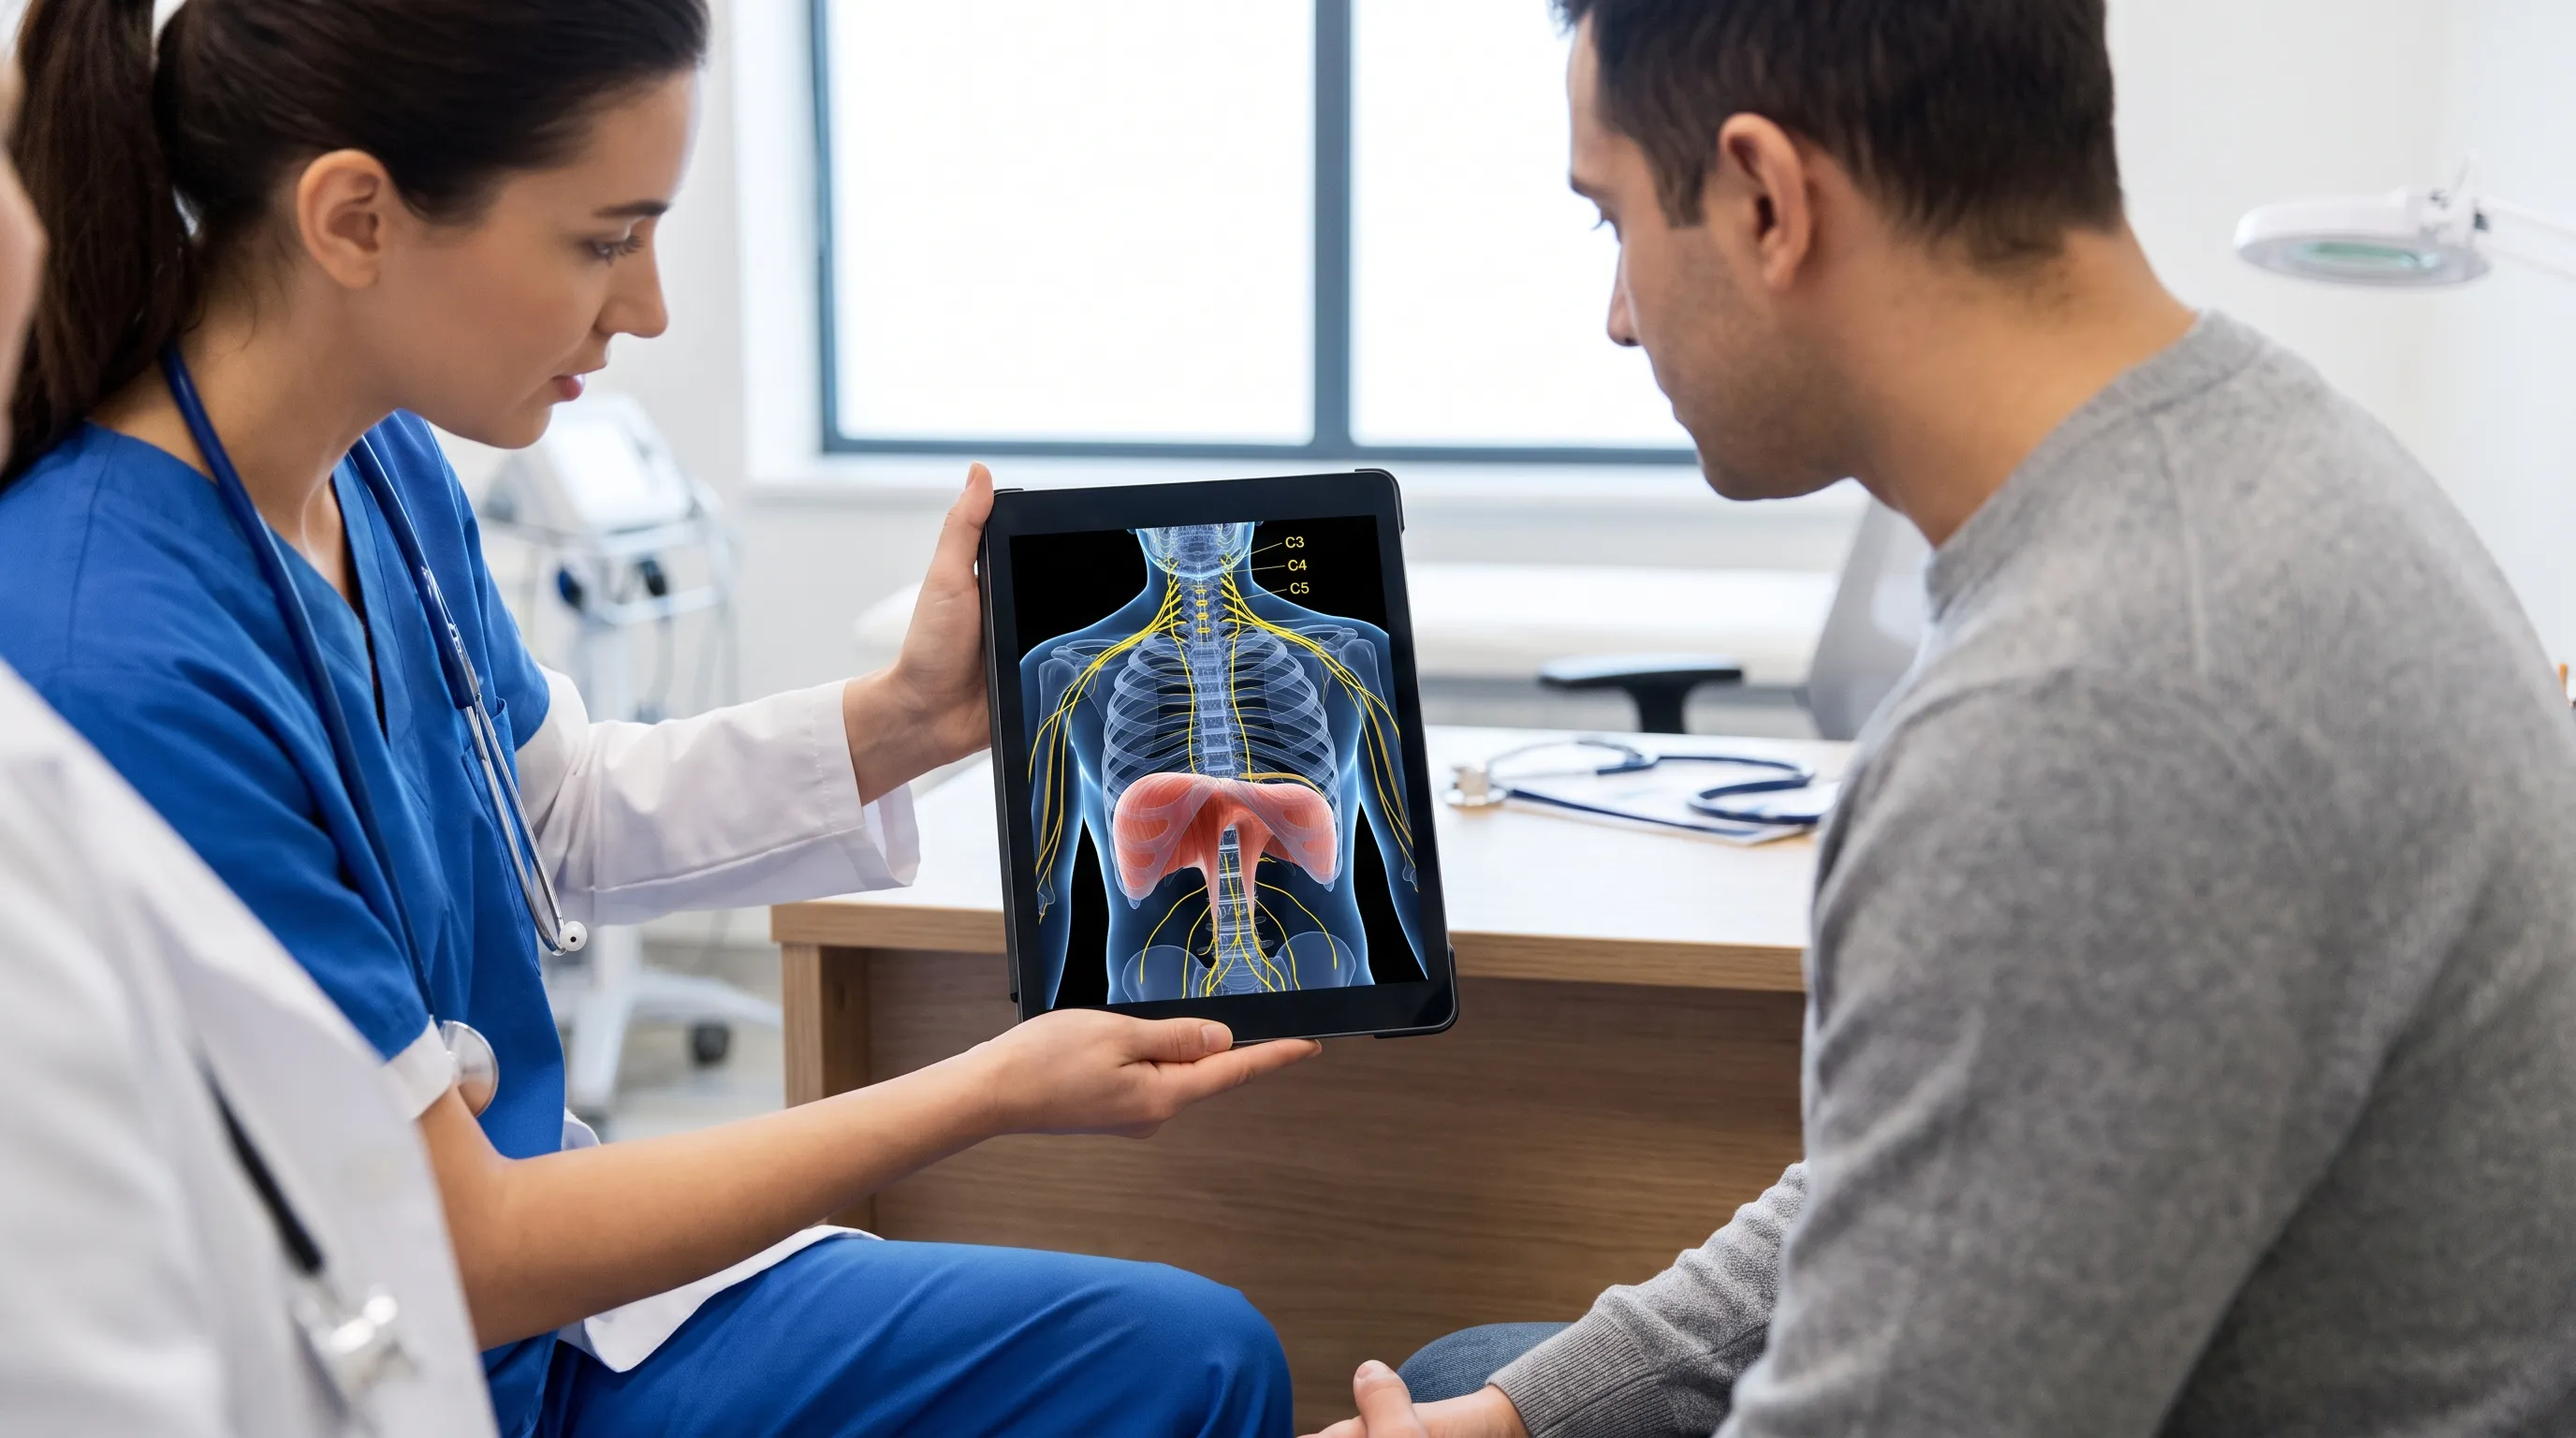
The human body is a highly interconnected biological network, where organs, nerves, and musculoskeletal structures communicate through complex signaling pathways. When gas accumulates in the gastrointestinal tract, it does not always remain confined to the stomach or intestines. Instead, it can create upward pressure against the diaphragm, a large, dome-shaped muscle that separates the thoracic and abdominal cavities. The diaphragm plays a crucial role in respiration and acts as a physical barrier between digestive organs and the lungs. However, this barrier is densely innervated by the phrenic nerve, which originates from the C3, C4, and C5 spinal nerve roots in the neck. Because the phrenic nerve transmits sensory information from the diaphragm directly to the cervical spinal cord, the brain occasionally misinterprets the origin of pain signals. This neurological phenomenon, known as visceral-somatic convergence, is the primary driver of gas pain in shoulder.
Free calculatorBMI CalculatorCalculate Body Mass IndexOpen the calculatorThe Phrenic Nerve and Cervical Cross-Talk
The phrenic nerve serves as a critical communication highway between the diaphragm and the central nervous system. When the diaphragm becomes irritated by trapped intestinal gas, inflammatory mediators, or direct mechanical pressure, the nerve sends pain signals upward. The cervical spinal cord processes these signals, but because it also receives input from the shoulder region, dermatomes C3 through C5, the brain defaults to a more familiar location. This referred pain pattern is a well-documented physiological response that frequently confuses patients and even some clinicians. The resulting discomfort can range from a dull, persistent ache to sharp, stabbing sensations that worsen with deep breathing or sudden movements. Recognizing that gas pain in shoulder originates from nerve cross-talk rather than musculoskeletal injury is essential for selecting appropriate treatment strategies.
Diaphragmatic Irritation and Visceral-Somatic Convergence
Visceral-somatic convergence occurs when sensory neurons from internal organs synapse onto the same second-order neurons in the spinal cord as those from the skin, muscles, and joints. The diaphragm shares embryological and neurological origins with structures that develop into the shoulder and neck region. Consequently, when gas expands the stomach or colon and pushes against the diaphragm, the resulting tension activates nociceptors that signal pain along the phrenic pathway. Patients often report discomfort localized to the left shoulder, particularly when the stomach or descending colon is distended, though right-sided gas pain in shoulder can also occur, especially with liver or gallbladder involvement. This bilateral referral pattern underscores the importance of a thorough clinical assessment to rule out localized pathology.
How Trapped Air Travels and Creates Pressure
Digestive gas originates from two primary sources: swallowed air and bacterial fermentation. When you eat quickly, drink through straws, chew gum, or consume highly carbonated beverages, excess air accumulates in the stomach. If the lower esophageal sphincter or pyloric valve restricts normal upward or downward movement, the gas becomes trapped. As the stomach or proximal small intestine distends, it presses against the inferior surface of the diaphragm. The resulting mechanical stretch activates mechanoreceptors and triggers the referred pain cascade. Over time, chronic gas retention can lead to diaphragmatic fatigue, altered breathing mechanics, and secondary musculoskeletal tension, further amplifying discomfort. Addressing the root cause requires understanding both gastrointestinal motility and postural habits.
Common Triggers and Gastrointestinal Contributors
While anatomical mechanisms explain why discomfort travels upward, identifying the specific triggers is crucial for long-term management. Several dietary, lifestyle, and medical factors contribute to excessive gas accumulation and subsequent diaphragmatic irritation. Recognizing these patterns allows individuals to implement targeted interventions and prevent recurring episodes of gas pain in shoulder.
Post-Surgical and Procedure-Related Gas
Minimally invasive surgical techniques, particularly laparoscopic procedures, require insufflation of the abdominal cavity with carbon dioxide to improve visibility. This intentional introduction of gas frequently escapes into the peritoneal cavity and settles beneath the diaphragm. Because carbon dioxide is highly soluble, the body eventually absorbs it, but the process takes several days. During this period, patients commonly experience significant gas pain in shoulder, which often peaks within 48 to 72 hours post-operation. The pain typically intensifies when lying flat and improves when sitting upright or leaning forward. Gradual mobilization, gentle walking, and heat therapy significantly accelerate gas reabsorption and reduce symptom duration. Understanding this predictable trajectory helps alleviate anxiety and prevents unnecessary diagnostic testing.
Dietary Habits and Fermentation Processes
The foods we consume directly influence gas production. Carbohydrates that resist digestion in the small intestine travel to the colon, where gut microbiota ferment them, releasing hydrogen, methane, and carbon dioxide. High-FODMAP foods, including certain legumes, cruciferous vegetables, dairy products, and artificial sweeteners, are particularly notorious for triggering excessive fermentation. Rapid consumption of meals, inadequate chewing, and frequent use of carbonated beverages compound the issue by introducing additional air into the digestive tract. When gas accumulates faster than the intestines can expel it, pressure builds and migrates upward. Modifying meal composition, pacing consumption, and identifying personal food intolerances are foundational steps in managing gas pain in shoulder.
Gastrointestinal Disorders and Functional Dyspepsia
Chronic digestive conditions frequently exacerbate normal gas production. Irritable bowel syndrome (IBS) alters gut motility and visceral sensitivity, causing even moderate gas volumes to trigger intense discomfort. Gastroesophageal reflux disease (GERD) and functional dyspepsia disrupt normal gastric emptying, allowing gas to pool in the proximal stomach. Small intestinal bacterial overgrowth (SIBO) represents another significant contributor, where abnormal bacterial colonization in the upper small intestine accelerates fermentation and gas generation. Individuals with these conditions often experience frequent episodes of gas pain in shoulder alongside bloating, altered bowel habits, and early satiety. Collaborative care involving gastroenterologists, registered dietitians, and physical therapists provides the most comprehensive approach to long-term symptom control.
Differentiating Gas-Induced Discomfort from Orthopedic or Cardiac Issues
Because shoulder pain can stem from numerous sources, accurate differentiation is essential. Musculoskeletal injuries, nerve compression, and cardiovascular events frequently mimic referred digestive pain. Misdiagnosis can lead to inappropriate treatment or delayed intervention for serious conditions. Understanding key clinical distinctions empowers patients to make informed healthcare decisions.
Musculoskeletal Strain Versus Visceral Referral
True shoulder injuries typically worsen with specific joint movements, weight-bearing activities, or direct palpation of the affected area. Pain from rotator cuff tears, bursitis, or cervical radiculopathy often radiates down the arm and correlates with mechanical stress. In contrast, gas pain in shoulder remains relatively constant regardless of shoulder movement but fluctuates with respiratory depth, body position, and bowel activity. Additionally, digestive-related discomfort often coincides with bloating, belching, or changes in bowel patterns, which are absent in primary musculoskeletal conditions. A simple positional test, such as lying flat versus sitting upright, frequently clarifies the pain origin.
Recognizing Critical Warning Signs
Certain symptoms require immediate medical evaluation, regardless of suspected digestive involvement. Chest pressure, shortness of breath, dizziness, profuse sweating, or pain radiating to the left jaw are classic indicators of cardiac ischemia. While gas pain in shoulder can occasionally cause chest tightness due to diaphragmatic tension, it does not typically present with systemic cardiovascular symptoms. Similarly, fever, jaundice, unexplained weight loss, or persistent vomiting suggest underlying pathology such as cholecystitis, pancreatitis, or gastrointestinal obstruction. When in doubt, erring on the side of caution and seeking emergency evaluation is always the safest approach.
| Feature | Gas-Related Shoulder Discomfort | Musculoskeletal Injury | Cardiac Warning Signs |
|---|---|---|---|
| Primary Location | Upper shoulder, often radiating to neck | Joint capsule, rotator cuff, or trapezius muscle | Center/left chest, radiating to arm/jaw |
| Movement Impact | Minimal change with shoulder motion | Significant worsening with specific movements | Unpredictable, often exertion-triggered |
| Associated Symptoms | Bloating, belching, flatulence, digestive changes | Localized swelling, clicking, range-of-motion limits | Sweating, nausea, shortness of breath, dizziness |
| Positional Response | Improves with upright posture, worsens when supine | Consistent regardless of torso position | Unchanged by posture, may improve with rest |
| Duration Pattern | Fluctuates with digestion, resolves in hours to days | Chronic or acute following trauma/overuse | Sudden onset, requires immediate attention |
When Shoulder Discomfort Signals Something Else
Persistent shoulder pain that does not correlate with digestive patterns warrants thorough clinical assessment. Cervical disc herniation, thoracic outlet syndrome, and adhesive capsulitis require specialized orthopedic evaluation. Additionally, gallbladder disease, peptic ulcer disease, and hepatic inflammation can present with referred shoulder pain through vagal and phrenic pathways. Diagnostic imaging, blood work, and targeted gastrointestinal studies help exclude these conditions. A systematic evaluation ensures that gas pain in shoulder is correctly identified while more serious etiologies are promptly addressed.
Evidence-Based Relief Strategies and Immediate Actions
When trapped air causes diaphragmatic irritation, swift intervention can significantly reduce discomfort. Evidence-supported techniques focus on promoting gas transit, relaxing the diaphragm, and modulating visceral sensitivity. Combining positional adjustments, breathing protocols, and targeted therapies yields the most reliable outcomes.
Positional Therapy and Gravity-Assisted Release
Gravity plays a powerful role in gas migration. Lying flat allows gas to pool beneath the diaphragm, intensifying nerve irritation. Shifting to a left lateral decubitus position aligns the stomach and colon anatomically, encouraging downward movement through the gastrointestinal tract. The knee-to-chest posture, commonly used post-surgery, creates gentle abdominal compression that facilitates gas expulsion. Alternating between gentle forward bending and supine positioning with a pillow under the hips prevents diaphragmatic stagnation. These techniques are particularly effective for managing acute gas pain in shoulder because they leverage anatomical positioning to redirect trapped air away from sensitive nerve receptors.
Diaphragmatic Breathing and Autonomic Regulation
Controlled breathing exercises directly influence phrenic nerve activity and gastrointestinal motility. Diaphragmatic breathing, also known as abdominal or belly breathing, activates the parasympathetic nervous system, reducing visceral hypersensitivity and promoting smooth muscle relaxation. To practice, place one hand on the chest and another on the abdomen. Inhale slowly through the nose, allowing the belly to expand while keeping the chest relatively still. Exhale gently through pursed lips, drawing the navel inward. Repeating this cycle for five to ten minutes lowers cortisol levels, decreases muscle guarding, and encourages coordinated intestinal peristalsis. Consistent practice significantly reduces the frequency and intensity of gas pain in shoulder.
Pharmacological and Botanical Interventions
Over-the-counter simethicone works by reducing surface tension in gas bubbles, causing them to coalesce and pass more easily. Activated charcoal adsorbs excess intestinal gas, though timing is critical to avoid medication interactions. Peppermint oil, standardized to 44 to 73 percent menthol, acts as a smooth muscle relaxant and reduces visceral spasm. Clinical trials demonstrate significant improvement in bloating and referred discomfort when enteric-coated capsules are taken before meals. Ginger tea and fennel seed extracts provide gentle carminative effects without pharmaceutical side effects. Always consult a healthcare provider before initiating new supplements, especially when managing chronic gastrointestinal conditions.
Dietary Optimization and Long-Term Preventative Measures
Sustainable relief from gas-related shoulder discomfort requires proactive dietary and lifestyle modifications. The gut microbiome, meal composition, and stress management collectively determine gastrointestinal gas production and motility efficiency. Implementing structured preventive strategies reduces recurrence and promotes overall digestive wellness.
The Role of the Low-FODMAP Framework
Fermentable oligosaccharides, disaccharides, monosaccharides, and polyols (FODMAPs) draw water into the intestine and rapidly ferment, producing substantial gas volumes. The low-FODMAP elimination diet, developed by Monash University researchers, systematically identifies individual trigger foods. After an initial two to six week restriction phase, foods are reintroduced gradually to determine personal tolerance thresholds. This evidence-based approach prevents unnecessary dietary restriction while effectively minimizing gas production. Many individuals with chronic gas pain in shoulder experience dramatic symptom reduction by identifying and moderating specific FODMAP intolerances.
Mindful Eating and Digestive Pacing
Rapid food consumption introduces excessive swallowed air and overwhelms digestive enzymes. Chewing each bite thoroughly stimulates saliva production, initiates starch breakdown, and reduces downstream fermentation. Eating smaller, more frequent meals prevents gastric overdistension and maintains consistent motility patterns. Avoiding straws, limiting carbonated beverages, and refraining from talking while chewing significantly reduce aerophagia. Allowing two to three hours between meals provides adequate time for complete gastric emptying, preventing overlapping digestive cycles that trap air. These simple behavioral adjustments consistently yield measurable improvements in digestive comfort.
Gut-Brain Axis Modulation for Chronic Sensitivity
Psychological stress profoundly alters gut motility, microbiome composition, and visceral pain perception. The enteric nervous system operates independently but communicates continuously with the central nervous system through the gut-brain axis. Chronic anxiety triggers sympathetic dominance, slowing intestinal transit and increasing gas retention. Incorporating stress-reduction practices such as progressive muscle relaxation, guided meditation, and regular moderate exercise restores autonomic balance. Cognitive behavioral therapy specifically targets visceral hypersensitivity, helping individuals recalibrate pain thresholds and reduce anticipatory anxiety around digestive symptoms. A holistic approach addressing both physical and psychological factors ensures lasting relief from gas pain in shoulder.

When to Seek Professional Medical Evaluation
While most digestive-related shoulder discomfort resolves with conservative measures, certain clinical indicators warrant professional assessment. Persistent symptoms lasting beyond one week, progressive intensity, or interference with daily activities suggest underlying pathology requiring diagnostic clarification. Healthcare providers may utilize abdominal ultrasound, comprehensive metabolic panels, hydrogen breath testing, or upper gastrointestinal endoscopy to evaluate structural and functional abnormalities. Collaborating with gastroenterologists, registered dietitians, and physical therapists ensures a multidimensional treatment plan tailored to individual physiology. Early intervention prevents chronic symptom escalation and supports optimal digestive recovery.
Frequently Asked Questions
Can trapped gas really cause shoulder pain without stomach symptoms?
Yes, referred pain from trapped digestive air can manifest solely in the shoulder region due to phrenic nerve irritation. The diaphragm shares nerve roots with the cervical spine, meaning abdominal pressure can trick the brain into localizing pain higher up, even without prominent gastrointestinal complaints. This neurological cross-talk is a well-documented physiological response that frequently surprises patients.
How long does gas pain in shoulder typically last?
In most cases, referred shoulder discomfort from trapped air resolves within 12 to 48 hours once the digestive system naturally expels the excess gas. Post-surgical patients may experience symptoms for a few days longer, depending on healing and mobility levels. Implementing positional therapy and gentle movement accelerates the natural reabsorption and elimination process.
Is gas pain in shoulder a normal symptom after laparoscopic surgery?
Absolutely. Insufflation with carbon dioxide during minimally invasive procedures frequently leads to diaphragmatic irritation. This post-operative shoulder ache is well-documented, usually peaking in the first 72 hours, and gradually subsides as the body absorbs and expels the residual gas. Surgeons routinely advise patients about this expected phenomenon to prevent unnecessary alarm.
Should I use heat or ice for referred shoulder discomfort?
Heat therapy is generally recommended for gas-related shoulder pain because it promotes muscle relaxation, improves local circulation, and helps ease diaphragmatic tension. Ice is typically reserved for acute inflammatory injuries or recent trauma, not visceral referral patterns. Applying a warm compress to the upper abdomen and shoulder simultaneously addresses both the source and the referred symptom.
Can stress or anxiety worsen gas-related shoulder symptoms?
Yes, psychological stress activates the sympathetic nervous system, which can disrupt normal gastrointestinal motility and increase visceral hypersensitivity. This often leads to prolonged gas retention, heightened diaphragmatic tension, and amplified perception of referred shoulder discomfort. Stress management techniques consistently improve both digestive function and pain tolerance over time.
Conclusion
Navigating gas pain in shoulder requires a comprehensive understanding of digestive physiology, neurological pathways, and targeted relief strategies. By recognizing the phrenic nerve connection, identifying dietary and surgical triggers, and implementing evidence-based interventions, individuals can effectively manage and prevent recurring episodes. Positional adjustments, controlled breathing techniques, mindful eating habits, and appropriate pharmacological support work synergistically to restore comfort and optimize gastrointestinal function. While most cases resolve spontaneously, persistent or worsening symptoms warrant professional evaluation to rule out underlying pathology. Empowering yourself with accurate medical knowledge and proactive self-care habits transforms temporary discomfort into manageable health awareness, ultimately supporting long-term digestive and musculoskeletal wellness.
How we work
Researched and drafted with AI assistance, then reviewed by a human editor against the cited sources.
This article is general health information, not medical advice. Consult a qualified healthcare professional about your own situation.