Carpal Tunnel Surgery Cost: Complete Financial & Guide

Waking up in the middle of the night to intense tingling, numbness, or aching pain in your wrist and fingers is a hallmark sign that your median nerve is struggling to function properly. For millions of Americans dealing with persistent carpal tunnel syndrome, conservative treatments like splinting, ergonomic adjustments, activity modification, and corticosteroid injections often provide only temporary relief. When symptoms severely impact daily activities, sleep quality, and professional performance, surgical decompression emerges as the definitive, evidence-based solution. However, navigating the financial landscape of orthopedic procedures can be just as daunting as the clinical decision itself. Understanding the carpal tunnel surgery cost is essential for patients who want to make informed, financially secure healthcare choices without compromising on surgical precision, patient safety, or long-term outcomes. In this comprehensive guide, we will break down every financial aspect of the procedure, from pre-operative diagnostics to post-operative rehabilitation, while providing actionable strategies to minimize out-of-pocket expenses and maximize lasting wrist health.
Understanding Carpal Tunnel Syndrome and the Need for Surgical Intervention
The Anatomy of Median Nerve Compression
Carpal tunnel syndrome develops when the median nerve becomes chronically compressed within the carpal tunnel, a narrow, rigid anatomical passageway located in the anterior aspect of the wrist. This compartment is bounded dorsally by the eight carpal bones and volarly by the transverse carpal ligament. The median nerve provides critical sensory innervation to the palmar surfaces of the thumb, index, middle, and radial half of the ring finger, while also supplying motor function to the thenar eminence muscles responsible for thumb opposition, abduction, and flexion. Chronic compression disrupts microvascular perfusion and axonal transport, leading to the classic triad of symptoms: nocturnal paresthesia, progressive grip weakness, and sensory discrimination deficits. Repetitive wrist flexion, prolonged exposure to hand-arm vibration, hormonal fluctuations during pregnancy, untreated diabetes mellitus, and hypothyroidism are well-documented physiological risk factors that exacerbate synovial hypertrophy and increase intra-tunnel hydrostatic pressure. The Mayo Clinic's comprehensive overview details how anatomical and systemic factors interact to create this debilitating condition. When the transverse carpal ligament fails to accommodate chronic pressure, conservative interventions lose their therapeutic efficacy, making surgical release a medically necessary and clinically indicated intervention.
Free calculatorBMI CalculatorCalculate Body Mass IndexOpen the calculatorWhen Is Surgery the Right Choice?
Determining the optimal timing for surgical intervention requires careful, evidence-based clinical evaluation. Electromyography (EMG) and nerve conduction velocity (NCV) studies represent the gold-standard diagnostic tools that objectively quantify the severity of demyelination, axonal loss, and distal motor latency prolongation. If electrodiagnostic testing reveals moderate to severe axonal degeneration, persistent symptoms lasting longer than six months despite rigorous conservative management, or visible clinical signs of thenar muscle atrophy, fellowship-trained hand surgeons strongly recommend operative release. Clinical guidance from the National Institutes of Health (NIH) emphasizes that early surgical intervention can halt progressive neuropathy, restore functional grip strength, and prevent irreversible motor denervation. Patients experiencing progressive hand weakness, frequent dropping of objects, constant numbness interfering with fine motor tasks, or debilitating sleep disruption should consult a board-certified specialist promptly. Delaying the procedure when clear clinical indicators point toward surgical necessity often results in prolonged pain cycles, secondary cervical strain from compensatory posture, and significantly extended rehabilitation timelines.
Carpal Tunnel Surgery Cost: A Comprehensive Financial Breakdown
National Average Pricing and Fee Structures
The financial reality of wrist surgery extends far beyond the operating surgeon's professional fee. A complete carpal tunnel surgery cost encompasses several distinct, independently billed components that collectively determine your final financial obligation. According to national healthcare pricing databases and transparency initiatives, the average total cost ranges from $2,800 to $7,200 for a unilateral procedure, though prices fluctuate based on facility accreditation level, metropolitan pricing indices, and surgical complexity. This aggregate figure typically includes the surgeon's professional fee, facility or ambulatory operating room charges, anesthesia services (either monitored anesthesia care or regional nerve block), pre-operative electrodiagnostic testing, and standardized post-operative follow-up visits. Surgeon fees alone average between $1,500 and $2,800, reflecting board certification status, years of specialized training, and case volume. Facility fees represent the largest variable, ranging from $1,000 to $4,500 depending on whether the procedure occurs in a hospital outpatient department versus an accredited ambulatory surgery center (ASC). Fair Health Consumer's transparent pricing database provides regional benchmarking data that empowers patients to anticipate realistic financial expectations and avoid billing discrepancies. Understanding these discrete cost categories is the first step toward requesting itemized estimates and structuring effective payment strategies.
Geographic and Facility-Based Price Variations
Healthcare reimbursement rates in the United States exhibit significant regional and institutional disparities. Urban medical hubs along the Northeastern corridor and Pacific coast typically operate with substantially higher real estate, staffing, and administrative overhead, translating to 20 to 35 percent higher procedural fees compared to Midwestern, Southern, and rural healthcare markets. Facility selection dramatically influences the final invoice. Accredited ASCs generally operate with optimized staffing models, streamlined supply chains, and focused procedural workflows, resulting in facility fees that are consistently 35 to 45 percent lower than hospital-based outpatient departments. Additionally, ASCs frequently offer transparent, all-inclusive bundled pricing models that package surgeon, facility, anesthesia, and standard post-operative care into a single predictable quote. The Healthcare Bluebook recommends patients prioritize Joint Commission or AAAHC-accredited surgical centers when clinical complexity allows, as this strategic facility choice can substantially reduce financial burden without compromising surgical sterility, equipment quality, or patient monitoring standards.

| Cost Component | Hospital Outpatient Department | Ambulatory Surgery Center (ASC) | Private Surgical Suite | Notes |
|---|---|---|---|---|
| Surgeon Professional Fee | $1,600 – $2,900 | $1,500 – $2,700 | $1,400 – $2,500 | Varies by board certification |
| Facility & Operating Room | $2,100 – $4,500 | $900 – $2,100 | $600 – $1,500 | Includes nursing & equipment |
| Anesthesia Services | $450 – $850 | $350 – $700 | $300 – $600 | MAC or regional block pricing |
| Pathology & Lab Review | $75 – $150 | $75 – $150 | $50 – $100 | If tissue specimen submitted |
| Total Unilateral Estimate | $4,150 – $8,250 | $2,750 – $5,500 | $1,700 – $3,100 | Pre-negotiated cash rates vary |
Hidden Fees and Unexpected Financial Liabilities
Many patients encounter billing surprises due to ancillary charges that are excluded from baseline surgical estimates. Pre-operative comprehensive metabolic panels, coagulation profiles, resting electrocardiograms for patients over 50, and specialized diagnostic ultrasound can collectively add $250 to $650 to the pre-operative phase. If anatomical variations require concurrent tenosynovectomy, flexor tendon gliding release, or ulnar nerve transposition, the carpal tunnel surgery cost increases proportionally to reflect additional operative time and specialized instrumentation. Furthermore, prescription neuropathic pain medications, custom-molded thermoplastic post-operative splints, and extended physical therapy regimens extending beyond the 90-day global surgical period are almost never bundled into the primary quote. Patients should proactively request an "all-inclusive" surgical package and explicitly verify whether the estimate covers post-operative emergency department visits for dressing complications or unanticipated wound care, as recommended by the Cleveland Clinic. Documenting these expectations in writing before scheduling protects against surprise medical billing and ensures complete financial transparency.
Insurance Coverage, Authorization, and Out-of-Pocket Planning
Navigating Deductibles, Copays, and Coinsurance Structures
Commercial health insurance fundamentally alters the financial trajectory of orthopedic procedures, but it rarely eliminates patient financial responsibility entirely. Individuals must meticulously review their policy's annual deductible status, copay schedule, and coinsurance percentages before authorizing surgical scheduling. If your annual deductible has not been fully satisfied, you will typically be responsible for paying 100 percent of the insurer's negotiated allowable rate until the threshold is met. Once the deductible is exhausted, standard coinsurance percentages apply, typically ranging from 20 to 40 percent of the allowed amount. For example, if the insurer establishes a $5,200 allowed rate for unilateral carpal tunnel release and your policy mandates 30 percent coinsurance, your out-of-pocket financial obligation would equal $1,560, provided your annual out-of-pocket maximum has not yet been reached. The Centers for Medicare & Medicaid Services publishes annual reimbursement updates and coverage determinations that directly impact orthopedic billing structures and patient cost-sharing. Policyholders should contact their insurance provider's clinical member services department to verify network participation, prior authorization requirements, and exact cost-sharing percentages before signing any surgical consent documents.
Prior Authorization and Medical Necessity Documentation
The vast majority of commercial carriers, Medicare Advantage plans, and employer-sponsored self-insured policies require explicit prior authorization before approving elective surgical interventions. This administrative prerequisite involves your orthopedic surgeon submitting comprehensive clinical documentation that definitively proves conservative modalities have been exhausted and that surgical decompression meets payer-specific medical necessity criteria. Failure to obtain or verify authorization status can result in automatic claim denial, leaving the patient contractually responsible for the entire procedural bill. Actionable tip: Request a printed or electronic confirmation containing your official authorization reference number, approved allowed amount, coverage start date, and any explicit clinical limitations before proceeding with scheduling. Maintain a personal archive of all supporting documentation, including electrodiagnostic reports, physical therapy discharge notes, corticosteroid injection records, and occupational restriction letters, as these documents form the evidentiary foundation of your medical necessity determination. If your initial submission is administratively denied, collaborate closely with your provider's billing specialists to initiate an expedited peer-to-peer clinical review or formal written appeal process.
In-Network vs. Out-of-Network Provider Verification
Selecting an in-network hand surgeon, anesthesiologist, and surgical facility represents one of the most effective, non-clinical strategies to systematically control the carpal tunnel surgery cost. Out-of-network specialists frequently charge above the insurer's usual and customary rate, and while federal legislation like the No Surprises Act provides robust protections against balance billing in emergency scenarios and certain non-emergent services performed at in-network facilities, elective procedures require proactive network verification and explicit consent. The American College of Surgeons strongly advises patients to independently verify network participation for all three primary billing entities: the operating surgeon, the attending anesthesiologist, and the facility itself. Even within a single hospital campus or medical office building, different specialists may maintain varying network contracts with identical insurance carriers. Always request a federally mandated Good Faith Estimate under the Transparency in Coverage regulations to establish clear financial boundaries and prevent unexpected billing disputes after the procedure.
Types of Carpal Tunnel Release Procedures and Clinical Implications
Open Carpal Tunnel Release: The Gold Standard Approach
Open carpal tunnel release (OCTR) remains the most extensively performed and clinically validated surgical technique globally, involving a single 2 to 3 inch curvilinear or longitudinal incision along the ulnar aspect of the palm to preserve the superficial palmar arch. The surgeon achieves direct, magnified visualization of the transverse carpal ligament, ensuring complete and controlled division while meticulously protecting the median nerve, recurrent motor branch, palmar cutaneous branch, and surrounding vascular structures. This method offers unparalleled anatomical exposure, making it the preferred approach for patients presenting with severe compressive neuropathy, altered wrist anatomy from prior trauma, rheumatoid synovitis, or concurrent tenosynovial pathology. Post-operative recovery typically requires two to three weeks of activity restriction, with progressive grip strength and pinch mechanics returning over a three to six month physiological remodeling phase. The open technique generally carries lower capital equipment costs compared to endoscopic alternatives, as it relies on standard hand instrumentation without disposable endoscopic portal systems. Clinical literature consistently demonstrates long-term symptom resolution rates exceeding 90 percent when performed by fellowship-trained specialists.
Endoscopic Carpal Tunnel Release: Minimally Invasive Technology
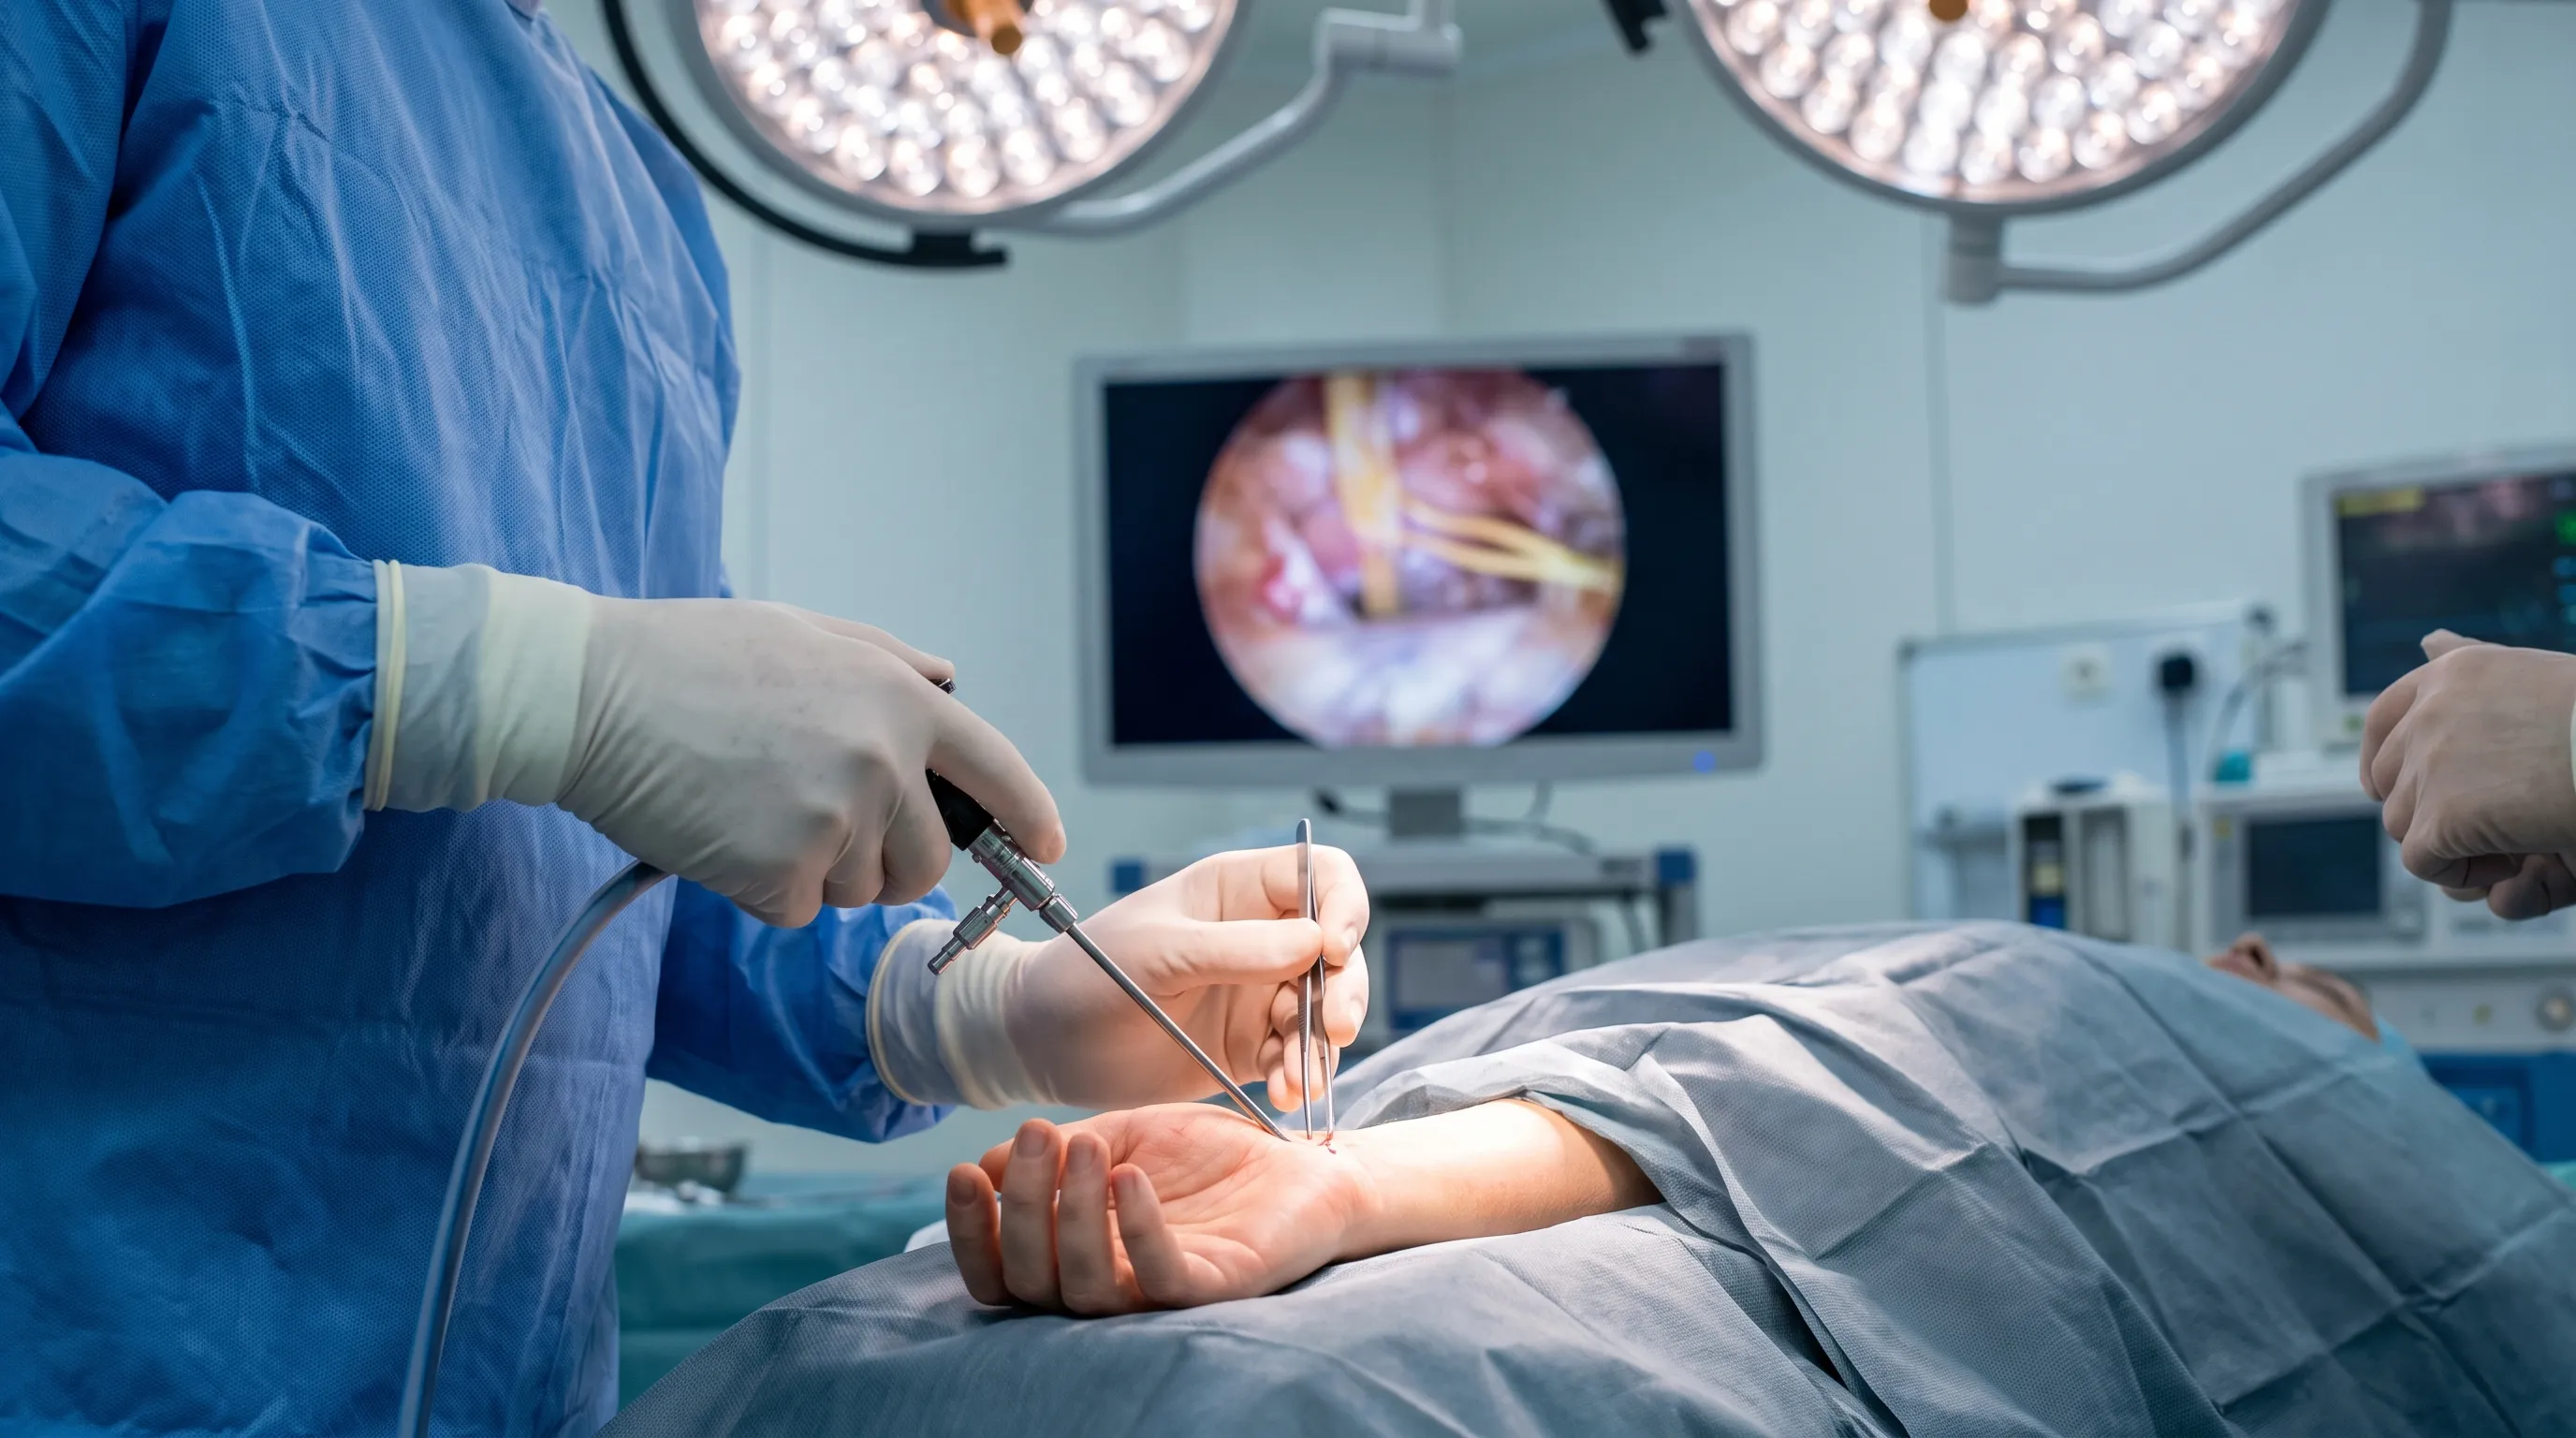
Endoscopic carpal tunnel release (ECTR) utilizes one or two smaller 1 to 1.5 cm proximal transverse incisions to introduce a high-definition fiber-optic camera system and specialized cutting instruments through a dedicated tissue portal. By projecting magnified anatomical visualization onto an external monitor, the surgeon safely divides the transverse carpal ligament from a subligamentous perspective, theoretically minimizing palmar soft tissue dissection, reducing postoperative wound pain, and decreasing pillar sensitivity. Patients frequently report accelerated functional recovery, particularly those employed in keyboard-intensive or fine-motor occupations, with many resuming light clerical duties within seven to ten days post-operation. However, the carpal tunnel surgery cost for ECTR can be 15 to 25 percent higher due to specialized endoscopic tower rental fees, proprietary disposable cannulas, and surgeon-specific procedural training premiums. While early functional milestones are well-documented, randomized controlled trials consistently demonstrate equivalent one-year clinical outcomes, grip strength restoration, and complication profiles when compared to open techniques. The American Society for Surgery of the Hand (ASSH) emphasizes that surgical approach selection should be dictated by anatomical suitability, diagnostic severity, occupational demands, and surgeon proficiency rather than perceived technological novelty alone.
Strategic Financial Planning and Budget Optimization
Step-by-Step Guide to Obtaining Accurate Cost Estimates
Accurate financial forecasting requires a systematic, documentation-heavy information gathering protocol. Begin by requesting the exact Current Procedural Terminology (CPT) codes from your surgeon's billing coordinator; the primary unilateral decompression code is typically 64721, with 64722 used if contralateral exploration is required. Contact your insurance member services department with the CPT code, place-of-service designation, and provider National Provider Identifier (NPI) number to receive your plan-specific allowed amount and projected patient financial responsibility. Request a written Good Faith Estimate directly from the surgical facility, as federal transparency regulations mandate this for both uninsured and self-pay patients seeking elective procedures. Compare at least three detailed quotes if geographically feasible, prioritizing ASCs that publish transparent, bundled pricing structures. Compile all financial projections into a structured tracking spreadsheet, explicitly differentiating facility overhead, surgeon professional fees, anesthesia professional fees, diagnostic prerequisites, and potential ancillary supply charges. This comparative analytical approach ensures complete transparency regarding the carpal tunnel surgery cost before signing surgical consent forms.
Negotiating Cash Discounts and Structured Payment Agreements
For patients electing to self-fund or confronting high-deductible commercial plans, direct financial negotiation frequently yields substantial monetary savings. Many accredited surgical centers and independent anesthesia groups offer 15 to 40 percent automatic discounts for upfront cash payments, certified cashier's checks, or verified debit transactions, as this payment method eliminates third-party billing overhead, collection agency risk, and insurance administrative processing delays. If immediate lump-sum payment is financially prohibitive, formally inquire about zero-interest installment payment plans administered directly through the facility's patient accounts department. While many centers partner with third-party medical financing companies offering credit lines, patients should rigorously compare promotional APR periods against traditional personal loans, home equity lines, or healthcare credit alternatives to avoid compounding interest liabilities after introductory periods expire. Actionable financial strategy: Ask the facility's financial counselor whether the institution participates in state-mandated charity care programs, income-based sliding scale fee structures, or municipal health assistance grants. Maintain written records of every financial conversation, including representative names, discussion timestamps, agreed-upon payment schedules, and discount authorization codes to prevent post-operative billing discrepancies.
Maximizing Tax-Advantaged Accounts and Employer Health Benefits
Strategic utilization of pre-tax healthcare funding mechanisms can substantially reduce the net economic impact of wrist surgery. Contributions to Health Savings Accounts (HSAs) and employer-sponsored Flexible Spending Accounts (FSAs) are explicitly exempt from federal income taxation, FICA taxes, and most state taxes, effectively reducing the real-world procedural cost by your marginal income tax bracket (typically 22 to 37 percent for most earners). Ensure you thoroughly understand your employer's FSA plan year rollover provisions, grace period extensions, or "use-it-or-lose-it" forfeiture clauses to prevent unutilized funds from being reclaimed at fiscal year-end. Additionally, certain employers offer supplemental Health Reimbursement Arrangements (HRAs) that can be strategically applied toward surgical deductibles, copay accumulators, or out-of-network balance bills. Employer-provided short-term disability insurance policies frequently replace 50 to 70 percent of gross wages during the initial two-week postoperative recovery phase, indirectly preserving household liquidity and preventing debt accumulation during reduced earning periods. Consult a certified financial planner or corporate benefits administrator to optimize pre-tax contribution timing and synchronize fund availability with your projected surgical calendar.
Postoperative Recovery Protocols and Long-Term Clinical Value
What to Expect During the First Twelve Weeks of Healing
Surgical decompression represents only the initial phase of a comprehensive, physiologically driven recovery process. Immediately following anesthesia emergence, patients are fitted with a sterile compressive dressing and a neutral-wrist thermoplastic splint to minimize postoperative edema, protect the volar incision from mechanical shear, and prevent excessive wrist flexion during early tissue remodeling. The initial 48 to 72 hours demand strict limb elevation above cardiac level to facilitate venous and lymphatic drainage, alongside scheduled non-steroidal anti-inflammatory medications and gentle, active distal phalangeal flexion and extension to maintain interphalangeal joint mobility and prevent tendon adhesions. Sutures or sterile skin adhesive strips are typically managed during the 10 to 14-day follow-up clinical visit. During weeks two through six, progressive tissue loading begins under the supervision of a certified hand therapist (CHT). Targeted scar mobilization, tendon gliding sequences, and progressive desensitization techniques prove crucial for restoring discriminative tactile function, preventing neuroma formation, and breaking established pain cycle feedback loops. By weeks eight to twelve, neurovascular remodeling typically stabilizes, allowing most patients to safely resume heavy manual labor, recreational athletics, and full occupational responsibilities. Rehabilitation adherence directly correlates with long-term functional outcomes and prevents chronic stiffness complications.
Physical Therapy, Ergonomics, and Preventative Maintenance Protocols
Sustained postoperative success depends heavily on long-term ergonomic modifications, targeted neuromuscular re-education, and proactive joint preservation strategies. Certified hand therapy not only restores baseline kinematics but also retrains maladaptive motor pathways that developed during months of chronic pain, compensatory grip modifications, and altered proprioceptive feedback. Patients should systematically invest in evidence-based workstation ergonomics, including split-mechanical keyboards, vertical or trackball mice, adjustable forearm supports, and anti-fatigue matting for standing workstations. The CDC recommends incorporating mandatory micro-breaks every 45 minutes, executing structured wrist flexor and extensor stretching routines, and maintaining strict neutral wrist alignment during manual tasks to dramatically reduce biomechanical stress on the median nerve tunnel. The American Physical Therapy Association publishes evidence-based hand rehabilitation protocols that patients can safely transition to independent home continuation programs following formal clinical discharge. Long-term preventative maintenance includes periodic occupational posture assessments, early intervention for recurrent inflammatory symptoms, and proactive management of systemic metabolic conditions that predispose to connective tissue hypertrophy.
Evaluating the Financial and Clinical Return on Investment
While the upfront carpal tunnel surgery cost necessitates careful financial planning and strategic resource allocation, the long-term physiological and economic benefits consistently validate the procedural investment. Chronic, untreated median nerve compression inevitably progresses toward irreversible thenar muscle denervation, permanent two-point discrimination deficits, and profound occupational earning limitations. Successful surgical decompression restores functional hand mechanics, eliminates debilitating nocturnal paresthesia, prevents secondary cervicobrachial compensation syndromes, and eliminates chronic reliance on neuropathic analgesics or repeated corticosteroid injections. From a macroeconomic perspective, the procedure typically achieves full financial breakeven within six to twelve months through restored workplace productivity, elimination of chronic pain management costs, reduced workers' compensation utilization, and prevention of long-term permanent partial disability classifications. Patients should fundamentally view this intervention not as an isolated medical expense, but as a strategic, high-yield healthcare investment in sustained manual dexterity, professional longevity, and comprehensive quality of life preservation.
Frequently Asked Questions
Is carpal tunnel surgery typically covered by insurance?
Yes, carpal tunnel release is widely covered by Medicare, Medicaid, and most commercial health insurance plans when medical necessity is clearly documented. Coverage requires evidence of failed conservative treatment, objective diagnostic testing confirming nerve compression, and functional impairment. Always verify your specific policy's deductible status, coinsurance requirements, and prior authorization protocols before scheduling the procedure to avoid unexpected out-of-pocket liabilities.
How much does carpal tunnel surgery cost without insurance?
The cash pay price for carpal tunnel surgery typically ranges from $2,800 to $7,200 per hand, depending on geographic location, surgical facility type, and whether an open or endoscopic approach is utilized. Ambulatory surgery centers often offer transparent bundled pricing, which can reduce self-pay costs by 25 to 40 percent compared to hospital outpatient departments. Always request a detailed, written good faith estimate and inquire about cash payment discounts.
Can I use my HSA or FSA to pay for carpal tunnel surgery?
Absolutely. Health Savings Accounts (HSAs) and Flexible Spending Accounts (FSAs) explicitly cover medically necessary surgical procedures, including carpal tunnel release, anesthesia fees, facility charges, prescribed postoperative medications, and physical therapy. Using pre-tax funds effectively reduces the real cost of the procedure by your marginal income tax bracket, making it one of the most financially efficient ways to manage surgical expenses.
Does the type of surgical technique affect the final cost?
Yes, endoscopic carpal tunnel release generally incurs higher facility and equipment fees compared to traditional open surgery due to specialized endoscopic instruments and camera systems. However, endoscopic techniques may reduce overall financial impact indirectly by enabling faster return to work and shorter physical therapy timelines. Your hand surgeon will recommend the most appropriate technique based on your anatomical requirements, clinical severity, and occupational needs.
Are there any hidden fees I should watch out for after surgery?
Patients should anticipate potential ancillary costs that fall outside the primary surgical quote, including pre-operative lab work, specialized postoperative splints, extended physical therapy sessions beyond the standard 90-day global period, and prescription medications. If additional concurrent procedures are performed or if surgical pathology review is required, separate billing codes may apply. Always request a comprehensive estimate covering all anticipated services.
Conclusion
Navigating the complex financial landscape of wrist surgery requires meticulous diligence, proactive healthcare planning, and a comprehensive understanding of clinical value versus procedural expense. By thoroughly demystifying the carpal tunnel surgery cost, patients can confidently structure informed treatment pathways that prioritize both fiscal responsibility and optimal anatomical outcomes. Successfully leveraging insurance benefit mechanics, negotiating transparent facility pricing, strategically utilizing tax-advantaged healthcare accounts, and selecting Joint Commission or AAAHC-accredited surgical environments dramatically reduces pre-operative financial anxiety. More importantly, appropriately timed surgical decompression restores essential manual dexterity, halts irreversible peripheral neuropathy progression, and safeguards long-term occupational earning capacity and personal independence. Schedule consultations with board-certified hand surgery specialists, verify all financial projections through written documentation, and commit to a structured, evidence-based postoperative rehabilitation protocol to guarantee that your healthcare investment yields lasting physiological restoration, professional stability, and uncompromised quality of life.
How we work
Researched and drafted with AI assistance, then reviewed by a human editor against the cited sources.
This article is general health information, not medical advice. Consult a qualified healthcare professional about your own situation.